
Features
‘Nobody is safe until everyone is safe’


The world faces a ‘catastrophic moral failure’ because of unequal COVID vaccine policies. With more than 80% of the COVID vaccines being given in high and upper-middle income countries, low-income nations are left at the receiving end with just 0.5 percent.
The inequitable distribution of vaccines have left the poor nations in the lurch and if the rich countries ‘keep their vaccine promises, the pandemic can end,’ observes the Director General of WHO, Dr. Tedros Ghebreyesus.
Randima Attygalle speaks to Dr. Palitha Abeykoon, World Health Organization (WHO) Director General’s Special Envoy to facilitate the COVID-19 response in Southeast Asia, for the latest developments of the pandemic which has taken a new shape, pushing countries to deploy new management strategies. Following are excerpts:
Q: With new COVID variants emerging, what are the predictions for both the world and us in the next few weeks and months and what precautions are encouraged?
A:
Considering the factors and trends in other parts of the world, particularly in India, we can talk of certain potentials. As a country, we managed both the first and the second waves relatively well with a ‘whole of society approach’; people and the government stakeholders, particularly the frontline health workers and defense personnel working together, standing on the same side. However, with the onset of the recent festive season, this ‘whole of society’ approach was slackened leading to this spike we are experiencing right now. Even in the case of India with some mammoth super-spreader events and dropping of the guard including non-observance of simple health protocols, a spike was inevitable. We are only hoping that it is only a spike and not a surge, both locally and globally.
Here at home, if the number of infected cases does not rise rapidly in the next two weeks, our health sector will be able to manage the situation, albeit with considerable strain, but if the numbers do not come down by the middle of next week or so, it will certainly lead to a deeply worrying situation.
 The evidence we have now reflects, (unlike in the first or second round), that the UK Variant of Concern (B1.117) is now established in Sri Lanka and with this virus the transmission is more efficient, more young people are infected, more serious complications are developed with more patients requiring oxygen and ICU facilities. If numbers increase, we will have a problem with capacity. The health sector is now setting up intermediate centers to isolate and treat patients, however, it will be a big strain on the system. Although we were fortunate to have vaccinated our frontline health workers and other personnel, we should not forget that they are working round the clock and are physically and even mentally exhausted. The logistical demands and shortcomings are an added burden on them.
The world still does not know enough about COVID 19 variants or the way the virus behaves, hence extreme precautions are necessary. The University of Jayewardenapura is doing a splendid job isolating the variants, particularly the variants of concern. We will need to do more sequencing which is a very expensive exercise. However, we cannot afford to neglect that also. There has been concern that some of the variants are not completely covered by some of the vaccines available; but this should not be much of a worry as the vaccines we use do give adequate protection, particularly preventing serious complications and death. Random testing in high transmission areas should also be given more muscle.
There is also this recent story in a reputed journal gaining ground that transmission is through aerosols in addition to being through droplets but research is still in process to establish it. In any event the key measures needed for preventing transmission in either case would be similar and are now well known.
Q: What lessons can we draw from India’s predicament?
A:
India is alerting us that ‘no one is safe unless everyone is safe.’ Being a large player in the drugs and pharmaceutical industry, India is today struggling to meet their health demands. With havoc in Delhi and Maharashtra, they do not have sufficient personal protection equipment, oxygen etc. We need to be mindful that the Indian situation can affect our supplies as well as we are a major importer of Indian pharmaceuticals and equipment.
Today the Indian health system is burnt out and this is an eye opener for us. We need to endeavour to prevent the Indian variant entering Sri Lanka and do more sequencing to determine if the new Indian variant (B. 1.617) which seems more virulent and produces serious complications, has entered the country.
In the past few weeks, we have been too lax and let our hair down too early and easily. The situation in India should push us to strengthen our ‘risk communication’ to the public.
Q: Do you think there is a need for tighter inter-province travel restrictions right now because despite warnings, people from ‘red zones’ such as Colombo still tend to flock into outstations?
A:
Yes, certainly there should be certain restrictions. In a country where the majority are daily wage earners, we cannot afford to go down for a long lock down risking the livelihood of thousands. What is needed is a balancing act for which selective lockdowns which are now in force and travel restrictions as indicated. There should also be other restrictions with regard to assembly, any type of gathering or ceremony and these restrictions should be strictly enforced. It is urgent that the transmission from ‘red zones’ to other ‘not-so vulnerable regions’ is suppressed. I reiterate that we cannot afford to overwhelm our health sector exceeding its capacities.
Q: What is the overall success rate of the vaccination programme world over?
A:
It is very clear that the countries which vaccinated more than 50% of their populations have demonstrated a lesser number of cases. In fact Israel has achieved nearly 85% of a roll out – the first country to achieve such a large number – and it is considered to have achieved ‘herd immunity’ and able to relax the earlier restrictions. For a while Israel has been reporting a very few cases and this is an example to the rest of the world. Even in England, the number of cases has come down, and can be attributed in some measure to the impact of the vaccination program, and so is the case in some of the states in the U.S.
Q: Many malpractices and managerial drawbacks were witnessed when the first dose of the Covax vaccine was locally administered. How important is it not to replicate these during a possible second roll out?
A:
If the programme stuck to its original mandate of vaccinating the frontline personnel and those over 60 years, it would have been much more successful because still the world over, most number of cases and deaths are reported among the elderly. With the initial mandate shifting from senior citizens, some people attempted to take advantage of the vaccination program and this was unfortunate. So prioritizing of the elderly and those with co -morbidities in the next phase of the program is still a must. We also need to prioritize factory workers and those who contribute significantly to the economy and among whom the spread of the infection is common.
Q: There is concern over the second dose with a possible shortage of vaccines. Where do we stand in this backdrop?
A:
Still there is an uncertainty about the quantity of the second doses which will be available, and whether we will receive these in time. I am aware of the efforts made by those responsible to ensure supplies for the second dose. We have already got around 600,000 doses of the Chinese Sinopharm vaccine which is awaiting WHO Emergency Use Listing which is likely to be obtained by the second week of May. (Our regulations require either WHO clearance or another similar stringent authority’s clearance for the administration of a new vaccine). We are also expecting the Russian Sputnik V vaccine in the next few weeks. With the possible arrival of these vaccines, we should be in a much better position within the next four to five weeks support the control of the spike to a limited extent and expand the vaccination program simultaneously.
Q: What are the other South East Asian countries which come under your purview that administer Chinese vaccinations and the Russian Sputnik V?
A:
The Maldives started administering the Chinese Sinopharm in small doses about two weeks ago. This vaccine was also gifted to Nepal and just a few days ago they commenced their roll out. Indonesia is using the other Chinese vaccine- Sinovac. Pakistan is using both Sinopharm and Sinovac. The Sputnik V is not yet being used in the region but it is likely that it will also soon get into the regional vaccine portfolio. Beyond the South East Asian region, the Chinese vaccines are also being used in the UAE, many South American countries and in certain parts of Africa.
Q: Bhutan is considered a model in COVID management efforts. Can you throw more light on this?
A:
It is indeed a model. Bhutan illustrates well how an enlightened leadership and a disciplined and sensible population managed to mitigate the risks and prevent the transmission and spread of the disease in the country. Bhutan prevented the infection coming into the country for a long time but it eventually did arrive there from the borders of her ‘big brothers.’ Nevertheless, they have been very successful in suppressing the virus. So far the country has only reported less than a thousand cases and just one death. It is also a country which has already vaccinated nearly 70% of their population, more than many of the developed countries. This is quite a feat.
Q: WHO Chief has expressed his concerns about the inequitable distribution of vaccines. In his recent report which appeared in the New York Times he had noted that if the rich nations ‘keep their vaccine promises, the pandemic can end.’ What are your thoughts?
A:
Although the rich countries talk of ‘One-health, universal health coverage’ etc. they have left only very few vaccines for the poor countries. More than 80% of the vaccines are found in the rich countries. This is a very sad situation and the rich countries should now ‘make a choice’ as the WHO Director General remarked. The ACT Accelerator (Access to COVID-19 Tools) was set up by a number of organizations including the WHO and European Commission and several more global bodies to enable tools such as vaccines, drugs, supplies and equipment to fight the pandemic. In fact the WHO has developed a fair allocation formula through the Covax facility. This global collaboration has worked to a large extent with regard to everything other than the vaccine distribution that was iniquitous. This is a serious problem and apart from the ethics and social justice, the rich countries should realize before it’s too late that they are not going to be safe until others are also safe. In economic terms alone too, the global economy cannot recover if there are serious disparities in vaccine coverage and it is a false economy for countries to do it alone.



(Excerpted from Madame-Sir, the autobiography of Manel Abeysekera)
On my return home from Oxford, I felt I should look around for a job. The first offer I had was made by Mr. J.L.M. Fernando, the then Chairman of Air Ceylon, who urged me to apply for an Executive Post with the Airline. I was about to do so when my eye caught a notification in the Ceylon Daily News, reproducing a Gazette notice calling for applications for the Ceylon Overseas Service (COS). Reading down the lines, a particular requirement set me thinking. It was that a married woman must obtain special permission of the Public Service Commission to join the Service. This made me realize that women could apply for a Service which had hitherto been a male bastion because recruitment was through the Civil Service Minute and Examination in which, as I have said earlier, the word “Man” did not embrace “Woman”.
So I obtained my parents’ permission to apply. I believe that Mother gave hers not really expecting me to be selected [no mother likes a daughter to go out into the world] while Father gave his in the fervent hope that I would be selected as that would be the next best thing to following in his footsteps and being in his own Ceylon Civil Service which I could not, being a woman. I remembered the Indian Foreign Service joke about our Foreign Service and hoped I could prove them wrong! I also hoped to do what Dame Janet wanted me to do and do what my women Indian Foreign Service friends were doing.
What I learnt after I joined the COS was that Mr. S.W.R.D.Bandaranaike, when he became Prime Minister and Minister of Defence and External Affairs in 1956, wanted young people to join the COS for its own sake as he himself was extremely interested in foreign affairs and, as in his domestic policy, desired to steer a new course which he believed would be for the good of the country. He had already changed our foreign policy of following British norms and practice and established relations with Eastern Europe, China, Africa, Latin America and the other countries of the Non Aligned Movement.
I was first interviewed by a panel of three Permanent Secretaries of which the Chairman was the Secretary of the Ministry of Defence and External Affairs, Mr. Gunesena de Soyza, who was subsequently appointed High Commissioner to Britain and who had earlier accompanied Mrs. Bandaranaike to Oxford as recounted by me. The other two were Mr.Alvapillai and Mr. Shelton Fernando. They welcomed me as the first woman to be interviewed for the service.
I recall Mr. Alvapillai being rather inclined to think that, since my parents had taken me abroad as shown in my application, I had acquired a taste for travel and wanted to see the rest of the world through the COS. When he enquired if that was so, I rather cheekily said that if I did want to merely travel abroad more, [there were no Exchange Control restrictions on obtaining foreign exchange for travel then], I could do so at father’s cost and not run the risks and hazards of the COS to do so. Again, when I was asked whether, should they take me in and train me at government cost, what would be the case if I decided to get married and leave the Service, it really put my back up and was perhaps the first time I felt a feminist! My reply was that any man they recruited could also leave at will and that there was no stipulation in the conditions of the Service that a woman could not marry and remain in the Service and that the choice was left to me and whoever I married!
I feel that my candour perhaps got me in, thanks to the fairness of the panel which did not resent my frank responses. [Initially, the India Foreign Service had the requirement that female officers had to retire on marriage and my IFS friend from Somerville Mira Malik, who was quite brilliant, had to do so though not so my other friend Soonu Kapadia who may have married later after the rule was rescinded. I like to think that I saved my female colleagues from the fate that befell Mira.
Mr Shelton Fernando, who had been up at Oxford, asked me whether I had not been tempted to caricature some of my lecturers and I am not surprised he did so as many of them were ideal subjects but, as I told him, I did not have the talent for it! I was also asked some foreign affairs questions which were not difficult to answer. The Chairman, Mr. Soyza had subsequently told Father that he had not seen such fine certificates as my Somerville Principal and Tutors had given me, for a long time-no doubt that they would have gone a long way in getting me into the COS and I am deeply grateful to them.
Next came the Public Service Commission interview. But before it, Mr. Eardley Gunewardena, Secretary to the Commission had called (my brother) Lakshman as a friend, to enquire whether I was really serious about wanting to join the COS, because I was the only woman who had qualified for interview and it would be a waste of the Commission’s time if I was not really keen. Lakshman informed him that I was quite serious about it as I had got my parents’ approval to apply for the Service.
This interview was more formal and less formidable than the previous one by the three Permanent Secretaries and I was fortunate to pass it and qualify for appointment to the COS as the first woman to do so. The medical examination that followed included a VD test which Mother strongly felt was degrading for me and I recall Father explaining to her that it was a rule that had to be complied
with and was no reflection on me! In order to pacify her, he said he would accompany me to the clinic so that everyone would see that I was not going there in secret!
Although I was rather quiet with people I did not know and my male colleagues did not quite know what to make of this puduma satha, they soon found out that I could take quite a lot of teasing and also give as good as I got! So we got on famously especially my batch of seven “Samurai” and me, who had busted the male bastion and become the first woman in the COS.
Briefings
The first “pep” talk we got was from the Permanent Secretary of the Ministry, Mr. Gunasena de Soyza. Something he said on that occasion has always remained with me. He informed us that we had been selected on certain criteria and for some special aptitude and individuality which the selectors had seen in us which they felt would be good for the Service. So he cautioned us that the Service did not expect us to become some kind of stereotype and that we should be ourselves and not think that even a cocktail party meant having a drink in one hand and making polite conversation alone they were intended to be avenues to make useful contacts, to engage in business where possible in a friendly, sociable way.
One of my batch mates’ name was Maurice Rabot and Mr. Soyza’s parting shot was: “I do not want the Rabots of the Service to become robots!” Anyway, I do not think that any of my batch mates could have ever become stereotypical diplomats as we were far too individualtistic for that! However, (my brother) Lakshman fondly called me a “diplomutt” and I do not think he would have called me that if I really were one; or rather I would like to think so!
Our next important briefing was by the Prime Minister and Minister of Defence and External Affairs himself, Mr. SWRD Bandaranaike. Before going to the Ministry that morning Father who had worked with the Premier as Commissioner of Local Government and later as Permanent Secretary when he was the Minister of Health and Local Government in the first Government at Independence under Premier Mr. D.S Senanayake as I have recounted, knowing him well, predicted that he would be in a bad frame of mind as he had placed senior members of the Federal Party, including Dr. E.M.V Naganathan, its Secretary, under house arrest and that it may impact on our meeting with him.
As we were about to enter the Premier’s Conference Room, my colleagues who had hitherto not politely stood aside for me as a woman now did so as they expected that then I would have to sit next to the Premier! But, when I entered the room and saw Mr. Soyza seated next to him I boldly walked up and sat next to Mr. Soyza causing one of my colleagues to have to sit next to the Premier!
How right Father was! The Premier made short shrift of us. Luckily he directed his question to my colleague seated on his left (where all of them had failed to manoeuver me!); he was asked to define his foreign policy and, before the poor man could stutter anything out, the Premier went on to the next and to the next! Finally, he sternly bade us read the recently published book on it and come back in a week’s time and we were only too glad to make our escape!
When the appointed day arrived, Father became the oracle again! This time he predicted that the Premier would be in a relaxed, expansive mood as the Federal Party members had been released and how right he was! As we walked in and sat down at the conference table, the Premier turned to Mr. Soyza and remarked: “Gunasena, I see you have taken a woman into the Service and that you are going to train them in foreign languages: I do hope the Tower of Babel will not become one of babble!” Everyone laughed including myself, suppressing the thought, “so much for gender equality and equity”, since my colleagues chattered as much as I did! His next remark was even more pointed: he asked Mr. Soyza “Who is the famous woman in international affairs with enormous fat legs?”
Of course it was Ms. Golda Meir, Foreign Minister of Israel at the time and later Prime Minister. Wasn’t I glad that my saree covered my own legs which I considered shapely “gams” in Hollywood jargon! I always thought that God had a sense of humour seeing that He had given me small hands and feet with what was in between being quite out of proportion! After Mother’s death as Father was heartbroken, he and I went on a trip to the Holy Land and, when we were in Israel [for which we had to have a separate passport so as not to have any evidence of it in the Arab countries], Father was invited to an Evening Reception by Foreign Minister Golda Meir to which I accompanied him where there were several dignitaries from Africa.
Each invitee was asked to stand to be introduced to the others and Father was introduced as the “Little Boy Scout from Ceylon”! But what fascinated me were her legs which were just as our Premier had described them! I also recall meeting Mr. Bandaranaike at a wedding reception and his speaking to me in French which he knew I would have learn to speak at Oxford for my Modern History course and my just getting away with it by replying that I was good at understanding French though not at speaking it. To my relief, he replied “Moi aussi”, meaning, ” Me too”!
Training
After these jokes, to my great relief, the Premier went on to discuss foreign affairs and his policy of non-alignment for Ceylon. These were the days of Sputniks and astronauts and the Premier had decided to give our batch [probably the first intake after he became Premier and Minister of Defence and External Affairs a really good training. In Parliament he stated that we should rise like Sputniks]. Perhaps he may have had ideas on how we should be placed as, except myself, all the others were over the normal maximum age for the joint Civil and Overseas Examination and maybe he thought we should be placed at a step higher than the first step of the Service depending on how we fared in our training. Be that as it may, we were assigned foreign languages and were to be sent to Oxford, Cambridge and London Universities to study them as well as diplomatic history, international relations, international law and other related subjects.
In my case, the assigning of a language and getting placement in a British University proved amusing. We were asked to indicate our first, second and third preferences from French, Italian, German, Russian and Chinese and I gave my choice as Chinese, Russian and German with an eye on being assigned to those countries, little knowing that logic did not always prevail in Foreign Services! I was first assigned German and then, for reasons unknown to me, I was assigned Italian. Now when the languages had first been assigned, the Foreign Ministry official entrusted with obtaining placements had got them and, when the languages were re-assigned, naturally re-assigned the names against the placements that had been obtained.
I was assigned Balliol College, Oxford, which the poor man was unaware was a men’s College [Oxford and Cambridge Colleges became co-ed comparatively recently] My batch mate Mahen Vaithianathan [son of Sir Kanthiah Vaithianathan, the first Permanent Secretary of the Ministry of Defence and External Affairs] who had been a year senior to me at Balliol and who had a puckish sense of humour, had taken the letter addressed to me as I happened to be on leave when they were handed out and, with great amusement, handed it to me the next day. It said, in typical “officialese” that I “should proceed to Balliol College, Oxford to study Italian”.
Equally amused as he, I took the letter to my senior colleague in charge of Overseas assignments, Arthur Basnayake of the first batch of officers and, with a very straight face, told him that I could not possibly “proceed to Balliol” although I would love to do so as Balliol had some showers as opposed to the rather unhygienic, traditional “English bathtubs”. Arthur was quite puzzled and asked me why not, especially as I had been at Oxford already.
My reply was that that was precisely why not and laughingly explained that Balliol would not have me as I was a woman! He laughed heartily and in a confidential whisper told me not to tell the press and of course I did not! The Ministry then quickly made amends and looked for a place and found one at New Hall [since -2008 re-named Murray Edwards College after its distinguished Founder President Dame Rosemary Murray – under whom I was privileged to be an alumnae – and the Refounders who made the endowment for its expansion]. I was delighted at not only having the joy of being at Cambridge but also because it was renowned for its School of Modern Languages. So I “proceeded to New Hall” to enter the Michaelmas [autumn] Term for one academic year.
Before we went abroad to our respective Colleges at the Universities of London, Oxford and Cambridge, we were sent to some of the important Government Departments relevant to our work such as Immigration and Emigration, Commerce, Tourism et al to orient us to their work and their relevance to our own work. Unfortunately, we were not able to go out into the provinces to be oriented to Kachcheri work as civil strife had broken out over the Tamil language issue. In the Ministry, our superb Consellor of training was the witty Glannie Peries who, I believe, was a Civil Servant who “manned” the Ministry before specific recruitment was made to it but preferred to continue in the foreign service. He imparted to us the finer points of foreign affairs including conduct at cocktail parties to which he had us invited for the purpose.

by Nilantha Ilangamuwa
They came. They ruined. They handed us back to the same old enemies. This is how a war supposedly fought for security can end, with a country left carrying the consequences long after the soldiers who invaded it have gone.
Twenty-five years after September 11, 2001, the American-led wars in Afghanistan and Iraq offer a record of military intervention that is impossible to separate from the destruction of institutions, displacement, sectarian violence and the weakening of societies that were supposedly being protected. Brown University’s Costs of War project estimates that the post-9/11 wars produced between 4.5 million and 4.7 million direct and indirect deaths and that more than 38 million people were displaced. Iraq remains the clearest example of how quickly the promise of security can become a prolonged political and human disaster.
The 2003 invasion was justified through the claim that Saddam Hussein possessed weapons of mass destruction and represented an urgent danger. The weapons were not found. The Iraq Survey Group did not discover an active Iraqi WMD stockpile, while later official investigations exposed serious failures in the intelligence used to support the pre-war case. Saddam’s dictatorship and previous use of chemical weapons were real. What collapsed was the proposition that Iraq possessed the active WMD capability used to justify invasion. Yet the war went ahead, and once it did, the United States faced the far more difficult question of what would replace the state it had destroyed.
The occupation did not simply remove Saddam Hussein and preserve Iraq’s governmental machinery. Coalition Provisional Authority Order No. 1 imposed sweeping de-Ba’athification, while Order No. 2 dissolved the Iraqi military and other state institutions. These were occupation decisions, not inevitable consequences of removing Saddam. The dissolution of the army was especially consequential. Hundreds of thousands of trained personnel suddenly lost employment, authority and their place in the new state. Not all had been committed Ba’athists. Many had joined the army as a profession. Removing the institution therefore did not remove military knowledge or political grievances. It scattered them into a country already filled with weapons, uncertainty and anger.
Former soldiers, Ba’athists, nationalists, Islamists, criminals and foreign jihadists became part of an expanding insurgency. Sunni resistance and al-Qaeda in Iraq grew amid the disorder, while sectarian militias expanded. The bombing of the al-Askari shrine in Samarra in 2006 helped unleash an extraordinary escalation of Sunni-Shia violence, turning Baghdad into a city of checkpoints, kidnappings, assassinations and death squads. The occupation had dismantled one of the state’s principal instruments of order without possessing a credible substitute.
The United States changed strategy. The 2007 surge, the Sunni Awakening and changes in military tactics reduced violence, but they did not create a durable political settlement. Sunni tribes that had fought al-Qaeda alongside American forces later felt marginalized by the government in Baghdad, creating grievances that were among the conditions exploited by the organization that evolved into Islamic State. It would be simplistic to say that America directly created ISIS. Its rise also depended on the Syrian civil war, the collapse of Syrian state authority, sectarian politics and decisions by Iraqi and Syrian actors. But the chain linking the 2003 invasion, the destruction of Iraqi institutions, the insurgency, al-Qaeda in Iraq and the later rise of Islamic State is part of the documented history of the organization. The irony is brutal. America invaded partly in the name of preventing terrorism, fought an insurgency that produced al-Qaeda in Iraq, later returned to fight the organization that emerged from that movement, and ultimately fought Islamic State in a country whose political order its own invasion had helped destroy.
The human cost extended beyond battlefields. On November 19, 2005, after a US Marine was killed by a roadside bomb at Haditha, Marines killed 24 Iraqi civilians, including women and children. The initial account did not accurately describe what had happened, and subsequent investigations produced criminal proceedings with varying outcomes. Abu Ghraib exposed an even wider crisis of detention, abuse and accountability. Photographs of prisoners being humiliated became symbols of an occupation that claimed to be constructing a democratic order.
Reconstruction brought another contradiction. The Coalition Provisional Authority controlled approximately $23 billion in Iraqi revenues and assets between May 2003 and June 2004, while the United States separately appropriated billions for reconstruction and security. The evidence does not support the crude claim that America simply stole Iraq’s oil, but the occupying authority exercised extraordinary control over a sovereign country’s finances while its institutions were being rebuilt. A huge contracting system followed, involving construction, logistics, security and maintenance, with oversight struggling to keep pace with enormous spending. The result was an economy dependent on oil and foreign-supported reconstruction. The World Bank estimates that in 2025 oil represented about 53 per cent of real GDP, 88 per cent of government revenue and 91 per cent of merchandise exports.
The consequences reached far beyond government accounts. The World Bank puts Iraqi unemployment at about 15.5 per cent in 2025 and identifies youth employment as a major structural challenge, while women remain dramatically underrepresented in the labour force. UNICEF says close to 3.2 million Iraqi school-age children are out of school and links the educational crisis to decades of conflict and under-investment. More than one million Iraqis remained internally displaced years after the territorial defeat of Islamic State.
The fact, however, is that Saddam’s Iraq had been a hostile barrier to Iranian regional influence. Its destruction removed that barrier, allowing political parties, religious networks and armed groups connected to Iran to become deeply embedded in the post-Saddam system. Some militias that fought American forces eventually became part of Iraq’s political and security architecture. Washington therefore removed an enemy of Iran and spent years confronting forces that benefited from the new order.
Here one cannot forget the irony in Afghanistan, the chokepoint of Bush-era war on terror policy, although its history is not identical to Iraq’s. America entered Afghanistan in 2001 to destroy al-Qaeda and remove the Taliban, remained for 20 years, built and armed Afghan security forces and spent enormous sums attempting to construct a new political order, only to withdraw in 2021 as the Taliban rapidly returned to power. In 2026, more than 2.6 million Afghan girls remain excluded from secondary education, while humanitarian agencies continue to report severe poverty and child malnutrition. Military force can achieve battlefield objectives. American forces defeated Saddam’s army within weeks, helped destroy Islamic State’s territorial caliphate and inflicted major losses on armed groups. The deeper failure was the inability to translate battlefield victories into political orders capable of surviving without foreign military power.
Iraq today is not the Iraq of 2006. Its government functions, cities have been rebuilt, its security forces have fought ISIS, and millions of Iraqis have rebuilt their lives. That resilience belongs to Iraqis themselves. But the dead cannot return, the displaced cannot recover the years they lost, children cannot reclaim the childhoods they spent amid violence, and institutions dismantled in 2003 cannot simply be restored to what they were before the invasion. The weapons that made the invasion supposedly urgent were not found. The urgency became war, the war became occupation, the occupation helped produce insurgency, and the insurgency helped produce another generation of extremists. The American military left, but the consequences remained. And after more than two decades, after the deaths of thousands and the destruction of a political order Washington claimed it could replace, American boots came off Iraqi soil last week, not as the triumphant conclusion of a successful mission, but as the final, deeply disgraceful image of a war whose consequences Iraqis will carry long after the last American soldier has gone.

Awareness for prevention
Dr. Niroshan Gamage
Director
National Anti – Rabies Campaign & Public Health Veterinary Services
Ministry of Health
Every year on 28 September, the world marks the anniversary of the death of Louis Pasteur, the scientist who gave humanity its first weapon against rabies. More than a century later, the weapon still works, and yet the disease still kills. In Sri Lanka, that quiet contradiction is the reason this year’s national theme is not a slogan about cure, but a call to action about prevention: Awareness for Prevention. Because in the story of rabies, the single most powerful drug is not found in a vaccine phial It is found in knowledge -the knowledge of what to do in the first fifteen minutes after a bite, and the will to act on it without hesitation. This is the story of how that knowledge, translated into a century of public health effort, has brought one small island nation to the very edge of eliminating one of humanity’s oldest and most feared diseases.
DISEASE OLDER THAN MEMORY
Few diseases have haunted the human imagination as persistently as rabies. For more than four thousand years, across nearly every continent, it has been recorded, feared, and mythologised the origin, some historians argue, of ancient legends about wolves, were wolves and the walking dead. Today, thanks to more than a century of vaccine science beginning with Pasteur’s 1885 breakthrough, rabies has been eliminated from Western Europe, North America, Japan, South Korea and parts of Latin America. Yet, it remains stubbornly endemic across large parts of Africa and Asia, killing tens of thousands of people every year most recent global estimates place the toll at over 44,000 annual deaths, a figure that public health authorities widely regard as a significant undercount given weak surveillance and routine misdiagnosis in the regions hit hardest.
The pattern of who dies is as telling as how many. Rabies is classified by the World Health Organization as a neglected tropical disease, and its victims are overwhelmingly the world’s poorest and most rural populations. More than eighty percent of cases occur in communities with little or no access to health education or post-bite treatment. Roughly four in every ten deaths are children under fifteen, small enough to be bitten while playing, and too young to know that a stray dog’s affectionate lick on a scraped knee can be a death sentence. The global economic toll, including medical costs, lost income and lost lives, is estimated at around US$ 8.6 billion a year. And in almost every case, the tragedy is one that modern medicine had already solved: 99 percent of human rabies cases trace back to the bite of a single, identifiable, preventable source – the domestic dog.
This is what makes rabies almost unique among fatal diseases. Once the virus reaches the central nervous system and symptoms begin, death follows in essentially 100 percent of cases; there is no cure, no rescue, no second chance. And yet the same disease is close to 100 percent preventable, provided the chain of prevention, wound care, timely treatment, and animal vaccination is never broken. Sri Lanka’s experience over the past half-century is one of the clearest demonstrations in the world of exactly how that chain can be built, and how easily it can fray.
SRI LANKA’S 130-YEAR BATTLE
Sri Lanka’s legal engagement with rabies is remarkably old, predating most of the country’s modern public health institutions by decades. The Rabies Ordinance No. 7 of 1893, “An Ordinance to provide for the Suppression of Rabies”, came into force on 2 January 1894, making it one of the earliest pieces of public health legislation in the island’s history. Governor Sir William Hercules Robinson pushed the law through after a spate of rabies cases alarmed the colony, granting local authorities the power to seize stray dogs, destroy diseased or suspected animals, and restrict dog movement during outbreaks. Amended repeatedly across the following century, elements of that 1894 framework remain part of Sri Lankan law even today, a striking legal thread connecting the present-day campaign to the nineteenth century.
For decades, rabies control amounted to little more than ordinance enforcement and dog destruction, with limited scientific basis and limited effect. Real change arrived only after the Second World War, when the newly formed World Health Organization began sending technical consultants to what was then Ceylon. On the advice of WHO rabies specialist Dr Ernest S. Tierkel, a dedicated Veterinary Public Health Unit was established under the Ministry of Health in 1953, the direct institutional ancestor of today’s Public Health Veterinary Services (PHVS), formally tasked with national rabies control since 1956.
The turning point came two decades later. In 1973, Sri Lanka recorded 377 human rabies deaths – the highest toll on record, and a national crisis that could no longer be managed through ordinance and culling alone. It became the trigger for the island-wide Rabies Eradication Program, launched in 1975 with WHO assistance and built, for the first time, on the modern pillars of mass dog vaccination, structured post-exposure treatment, and public education. From that peak, deaths fell below 100 by the late 1980s and have continued a broadly downward trend ever since interrupted, time and again, by periods of reduced funding or disrupted vaccination coverage that forced the programme to adapt.
HOW RABIES SPREADS
Rabies is a viral infection of the central nervous system, transmitted almost always through the saliva of an infected mammal typically via a bite, though scratches or licks on broken skin or mucous membranes such as the eyes or mouth can also carry the virus. The incubation period is unpredictable, typically two to three months but ranging from as little as one week to as long as a year, depending on factors including the location of the wound and the size of the viral dose. Early symptoms are deceptively generic: fever, general pain, and an unusual tingling or burning sensation at the site of the original wound. As the virus advances toward the brain and spinal cord, the disease progresses to one of two clinical forms.
Furious rabies, the more commonly recognised form, produces hyperactivity, agitation, hallucinations, and the hallmark symptoms of hydrophobia – a terror of water – and aerophobia, a fear of drafts of air, with death typically occurring within days from cardio-respiratory arrest. Paralytic rabies, accounting for roughly one in five human cases, follows a quieter but no less fatal course: muscles gradually become paralyzed starting from the wound site, a coma slowly develops, and death follows. Because it lacks the dramatic hallmark symptoms of the furious form, paralytic rabies is frequently misdiagnosed, contributing to the systematic under-reporting of the disease worldwide.
Laboratory surveillance conducted by the Medical Research Institute over multiple study periods has consistently found that dogs account for roughly 85 to 97 percent of confirmed rabies-positive samples in Sri Lanka, with cats a distant second at somewhere between 2 and 8 percent. Cattle, goats and other livestock occasionally test positive, though usually after being bitten by a rabid dog rather than acting as an independent source of human infection. Wild carnivores chiefly mongooses, and more rarely civets and jackals account for only a small fraction of confirmed cases, though the confirmation of sylvatic, wildlife-cycle rabies in a civet in Moneragala District some years ago served as a reminder that a wildlife reservoir cannot be entirely ruled out. In practical terms, however, the domestic dog remains both the overwhelming source of the problem in Sri Lanka and the single most effective point of intervention. (See Figure 1)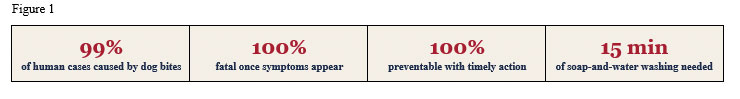
THE FIVE PILLARS OF PREVENTION
If Sri Lanka’s public health message for World Rabies Day 2026 can be reduced to a single idea, it is this: prevention is not one action but a chain, and every link in that chain depends on people knowing what to do and acting immediately. Five pillars make up that chain — and every one of them begins, or ends, with awareness.
1. Wash First: The Single Most Powerful First Response
If Sri Lanka’s public is to remember one instruction this World Rabies Day, it should be this: immediately and thoroughly wash any bite or scratch wound with soap and running water for a full fifteen minutes. This single act, so simple that it costs nothing and requires no medical training, physically flushes and inactivates a significant proportion of the virus at the wound site before it can travel toward the nervous system. Povidone-iodine or a similar antiseptic can be applied afterward if available. Wound washing is not a substitute for medical care, it is the first, most time – critical step of it, and delay of even a few hours reduces its protective value. Every household, every school, every workplace in Sri Lanka should treat this instruction with the same reflexive urgency given to calling for an ambulance.
2. Seek PEP Without Hesitation
Washing the wound buys time; post-exposure prophylaxis (PEP) is what completes the job. PEP is the emergency medical response administered after a bite, calibrated to the severity of exposure. Category I contact – licks on intact skin – requires no vaccination. Category II exposures, such as minor scratches or nibbling without bleeding, call for wound washing and immediate vaccination. Category III exposures – bites that break the skin, multiple wounds, or contamination of mucous membranes – require wound washing, a full vaccine course, and, where indicated, rabies immunoglobulin or monoclonal antibodies infiltrated directly into the wound. In Sri Lanka, this treatment is provided free of charge through government hospitals, under national clinical guidelines that have been refined since 2002. The message for the public must be unambiguous: any bite or scratch from a dog, cat, or other mammal, however minor it appears warrants an immediate visit to a health facility. Assuming a wound is “too small to matter” is the single most dangerous misjudgment a bite victim can make.
If You Are Bitten or Scratched
•Wash the wound immediately with soap and running water for 15 minutes.
•Apply povidone-iodine or an antiseptic if available – do not apply oil, chilies, herbs or other folk remedies.
•Go to the nearest government hospital without delay, even for a minor wound.
•Report the animal, if possible, for observation or testing.
•Complete the full course of vaccination exactly as prescribed – do not stop early.
3. Vaccinating the Source: Dogs Protect People
Treating bite victims saves individual lives; vaccinating dogs saves entire communities, because it interrupts transmission at its true source. Mass dog vaccination is recognised globally, and confirmed repeatedly in Sri Lanka’s own data, as the single most cost-effective rabies control intervention available. he national experience of the past decade makes the case with striking clarity.
The national vaccination and mortality figures for the past eleven years illustrate both the scale of the effort and its results (See Table 1):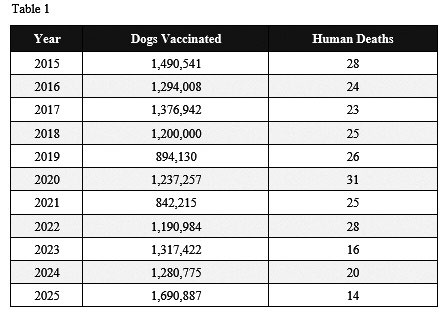
The pattern is instructive. The dip in vaccinations around 2019–2021 – a period disrupted by economic crisis and pandemic-era resource constraints coincides with a rise in human deaths back toward thirty a year. The sharp recovery in 2023–2025, culminating in nearly 1.7 million dogs vaccinated in 2025, corresponds with the lowest death toll in the eleven-year series: just 14. Few relationships in Sri Lankan public health are documented this cleanly. Every dog vaccinated is a measurable unit of protection for the humans who share its street, its temple, and its schoolyard.
4. Managing the Dog Population, Humanely
Vaccination alone is not sufficient without a sustainable strategy for the free-roaming dog population that vaccination teams must repeatedly reach. Since 2007, Sri Lanka has followed a formal “No Kill” policy, replacing culling that long proven ineffective at controlling rabies with animal birth control through sterilization and, where appropriate, hormonal contraception. A stable, sterilized, and vaccinated dog population is easier to protect, easier to monitor, and far less likely to sustain a rabies transmission cycle than an unmanaged, rapidly reproducing one.
One of the more remarkable chapters in this pillar unfolded in Puttalam District, where oral rabies vaccination, a technique for immunizing dogs too wary or too free-roaming to be caught by injection teams was pioneered in Sri Lanka by Dr P. A. L. Harischandra. By 2003, the technique achieved more than 75 percent vaccination coverage in the district, offering a template later drawn upon elsewhere in the country for reaching the hardest population of all to access: the ownerless, free-roaming dog. Responsible pet ownership, leashing, confinement, and ensuring every owned dog is both vaccinated and sterilized remains the public’s essential personal contribution to this pillar.
5. Awareness: The Multiplier Behind Every Other Pillar
Wound washing, PEP-seeking behaviour, dog vaccination uptake, and responsible pet ownership share a common precondition: people must know what to do, and believe it matters enough to do it immediately. This is why Sri Lanka’s 2026 theme places awareness at the center rather than the margins. Public education in schools, in clinics, in community and religious gatherings, and increasingly through digital and social media teaches recognition of dog behaviour and bite risk, correct first-aid response, and the location of the nearest treatment facility. It replaces dangerous folk remedies with evidence-based action, and it converts a frightened bystander into a capable first responder within the critical first minutes after an exposure. Awareness does not compete with vaccines and antiserum for importance; it determines whether those tools are ever reached in time.
Every action taken in the first fifteen minutes after a bite is a life protected. Awareness is the tool that ensures that action is taken.
2025 vaccination figures, the highest in the eleven-year dataset, together with the lowest recorded death toll, reflect a period of renewed operational intensity for the anti-rabies campaign, following a difficult stretch during the years of economic constraint. Surveillance, though historically fragmented across PHVS, the Medical Research Institute, and the Department of Animal Production and Health, has gradually improved, notably with animal rabies becoming a notifiable disease in 2012 the human cases have been notifiable since 1971.
TOWARD ZERO BY 2030
In 2015, WHO, FAO and WOAH jointly set a global target of zero human deaths from dog-mediated rabies by 2030. Sri Lanka initially aimed higher, publicly committing in 2016 to eliminate human rabies deaths by 2020, a target later judged, along with those of other South Asian countries, to be unrealistic, and formally reset to the global 2030 horizon following a regional SARE (Stepwise Approach towards Rabies Elimination) assessment workshop held in Colombo in 2019.
Achieving that goal will require Sri Lanka to close several persistent gaps: fragmented data-sharing between PHVS, the Medical Research Institute and the Department of Animal Production and Health; incomplete and sometimes inconsistently funded sterilization coverage; and the unresolved institutional question raised again in the ongoing proposal to transfer rabies-control functions from the Ministry of Health to the Ministry of Agriculture, Livestock, Lands and Irrigation a debate, ultimately, about which ministry is best placed to lead a disease that sits squarely at the intersection of animal and human health.
More than 130 years after the 1894 ordinance first gave the state the legal power to act against rabies, Sri Lanka is closer than it has ever been to eliminating human deaths from the disease. The 2025 figures record vaccination coverage and the lowest death toll on record offer genuine grounds for optimism. Whether that momentum can be sustained through to 2030 will depend on exactly the same ingredients that have driven every previous gain in this history: consistent funding, high dog-vaccination coverage, and institutional continuity for the agency tasked with carrying the work forward.
This World Rabies Day, the call to action is addressed to every household, school and community in Sri Lanka. Wash every wound. Seek treatment for every bite, however small. Vaccinate every dog, owned or community. Support humane, sustained population management. And talk about it because the awareness that reaches a neighbour, a child, or a stranger before the next bite occurs may be the single intervention that decides whether the story ends in recovery, or in tragedy.
Wash the wound. Seek PEP. Vaccinate your dog. Manage the population humanely. Spread awareness.
That is what “Awareness for Prevention” means and it is how Sri Lanka reaches zero.

THE SLFUW CELEBRATES 85th ANNIVERSARY

Oshini and Yenuthi excel as SL women strike Chess Olympiad gold

The first woman in the foreign service or Ceylon Overseas Service it was then called

They Came. They Ruined. They Left

Pathfinder Foundation and the China Center for South Asian Studies at Sichuan University launch the Colombo Maritime Dialogue 2026 Report

Peradeniya alumni help repair Ditwah damage on campus

‘Dates have the highest sugar content to fight Coronavirus’

Sunday Island 27 December – Headlines

#SundayIsland 17th December – Headlines

Sunday Island – 28th March

Sunday Island Headlines – 21 March

Sunday Island – 21st February – Headlines
-

 News6 days ago
Police remove Thileepan statue in Jaffna
-

 Features6 days ago
The 22nd Amendment, constitutional recovery and illiberal slippage
-

 Features6 days ago
Of foreigners as CEOs of Lankan ventures
-

 Latest News4 days ago
Gold winner Tharanga gets brand-new Honda Vezel from SLAAJ
-

 News6 days ago
Sajith rejects Jt. Opp. protest sabotage claim; SJB TU chief demands remedial action
-

 Features4 days ago
Why Sri Lanka needs an Inclusive Civic Nationalism – urgently
-

 Features5 days ago
Thailand’s biggest new global star …
-

 News3 days ago
US-assisted ‘Ice’ detection: NPC to examine IGP’s move to transfer drug-busting team